Showing posts with label Medications. Show all posts

Sunday, May 22, 2011

Top 10 Most Prescribed Medications

According to a report from the IMS Institute for Healthcare Informatics, the top 10 most-prescribed drugs in the U.S. are:

- hydrocodone (combined with acetaminophen)
- simvastatin
- lisinopril
- levothyroxine sodium
- amlodipine besylate
- omeprazole
- azithromycin
- amoxicillin
- metformin
- hydrochlorothiazide

The top 10 best-selling drugs are:

- Lipitor, $7.2 billion
- Nexium, 6.3 billion
- Plavix
- Advair Diskus, $4.7 billion
- Abilify
- Seroquel
- Singulair, $4.1 billion (it will be generic in 2012)
- Crestor
- Actos
- Epogen

References:
The 10 Most Prescribed Drugs. WebMD.
Image source: Wikipedia, public domain.

Tuesday, March 22, 2011

When physicians prescribe a new medication... confusion ensues

According to a 2006 study of physician-patient communication during primary care visits, when physicians prescribed a new medication they:

- did not tell the patient the name of the new medication in 26% of the cases (the other way to look at the data is that the physicians stated the specific medication name for 74% of new prescriptions)

- did not explain the purpose of the medication to patients in 13% of cases (explained the purpose of the medication for 87%)

- did not tell patient about adverse side effects of the medication in 65% of cases

- did not describe to patients how long to take the medication in 66% of cases

- did not tell patients the number of pills to take in 45% of cases

- did not tell patients about medication dosing and timing in 42% of cases

References:
Physician Communication When Prescribing New Medications. Arch Intern Med. 2006;166:1855-1862.
Image source: Wikipedia, public domain.

Monday, November 8, 2010

Liraglutide (Victoza) superior to sitagliptin (Januvia) for reduction of HbA1c in diabetics


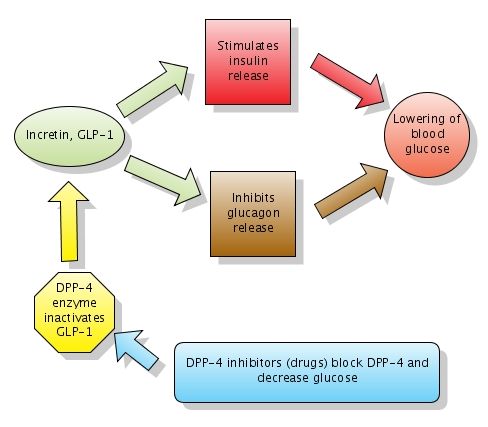
Action of DPP-4 inhibitors. Note that DPP-4 normally inactivates GLP-1. DPP-4 inhibitors block DPP-4 which in turn leaves GLP-1 active. Click to enlarge the figure. Created with Gliffy.

What is Glucagon-like peptide-1 (GLP-1)?

Glucagon-like peptide-1 (GLP-1) is a GI peptide that stimulates insulin secretion (similar to sulfonylureas). GLP-1 also inhibits glucagon release, gastric emptying and food absorption. GLP-1 and another similar peptide are called incretins. As noted above, incretins have a dual action which leads to lowering blood glucose:

1. Stimulate insulin release
2. Inhibit glucagon release

Exenatide (Byetta) is a GLP-1 receptor agonist approved for adjunctive therapy for patients with DM 2 who are not well controlled on oral agents. It is available only as injections and has to be administered twice daily.

DPP-4 inhibitors, or gliptins, increase GLP-1 levels by blocking the enzyme which inactivates GLP-1. The enzyme is called DPP-4 (dipeptidyl peptidase-4). They act similarly to Byetta (see figure above) but have the big advantage to be available in oral form (pills). Gliptins used for treatment of DM2 include sitagliptin (Januvia) and vildagliptin (Galvus).

What is Liraglutide?

Liraglutide (Victoza) is a long-acting glucagon-like peptide-1 (GLP-1) analog that was developed by Novo Nordisk for the treatment of type 2 diabetes. Liraglutide has a half-life after subcutaneous injection of 11–15 hours, making it suitable for once-daily dosing (in contrast to Byetta's twice daily).


Liraglutide. Image source: Wikipedia, public domain.

Liraglutide (Victoza) superior to sitagliptin (Januvia) for reduction of HbA1c in diabetics

This Lancet study assessed the efficacy and safety of the human GLP-1 analogue liraglutide versus the DPP-4 inhibitor sitagliptin, as adjunct treatments to metformin, in individuals with type 2 diabetes who did not achieve adequate glycaemic control with metformin alone.

More than 600 participants (aged 18—80 years) with type 2 diabetes mellitus who had inadequate glycaemic control (glycosylated haemoglobin [HbA1c] 7·5—10·0%) on metformin (more than 1500 mg daily) were enrolled.

Participants were randomly allocated to receive 26 weeks' treatment with 1·2 mg or 1·8 mg subcutaneous liraglutide once daily, or 100 mg oral sitagliptin once daily.

Greater lowering of mean HbA1c (8·5% at baseline) was achieved with 1·8 mg liraglutide (−1·50%) and 1·2 mg liraglutide (−1·24%) than with sitagliptin (−0·90%).

Nausea was more common with liraglutide (27%) on 1·8 mg. Minor hypoglycaemia was recorded in about 5% of participants in each treatment group.

Liraglutide was superior to sitagliptin for reduction of HbA1c, and was well tolerated with minimum risk of hypoglycaemia. These findings support the use of liraglutide as an effective GLP-1 agent to add to metformin.

References:

Tuesday, October 5, 2010

Beyond statins: Thyromimetic eprotirome decreases LDL

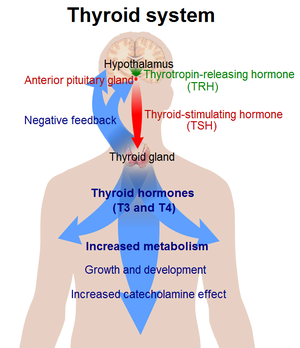
Dyslipidemia increases the risk of atherosclerotic cardiovascular disease and is incompletely reversed by statin therapy alone in many patients. Thyroid hormones lower levels of serum low-density lipoprotein (LDL) cholesterol and has other potentially favorable actions on lipoprotein metabolism. Consequently, thyromimetic drugs hold promise as lipid-lowering agents if adverse effects can be avoided.

In this 12-week trial, the thyroid hormone analogue eprotirome was associated with decreases in levels of atherogenic lipoproteins in patients receiving treatment with statins.

Similar reductions were seen in levels of serum LDL, apolipoprotein B, triglycerides, and Lp(a) lipoprotein. No change in levels of serum thyrotropin or triiodothyronine was detected, although the thyroxine level decreased in patients receiving eprotirome.

References:
Image source: Wikipedia, public domain.

Tuesday, September 14, 2010

"Professional Guinea Pigs" in Clinical Trials - TIME video


Human subjects are paid in Phase 1 clinical trials to test the toxicity levels of new drugs. Some make a profession out of it, but researchers worry about health risks.

References:
Clinical Trials: Professional Guinea Pigs. TIME.

Monday, July 19, 2010

Mipomersen - antisense technology to lower LDL cholesterol

Homozygous familial hypercholesterolaemia is a rare genetic disorder in which both LDL-receptor alleles are defective, resulting in very high concentrations of LDL cholesterol in plasma and premature coronary artery disease. This study investigated the use of an antisense inhibitor of apolipoprotein B synthesis, mipomersen, to lower LDL cholesterol.

Patients aged 12 years and older who were already receiving the maximum tolerated dose of a lipid-lowering drug, were randomly assigned to mipomersen 200 mg subcutaneously every week or placebo for 26 weeks.

34 patients were assigned to mipomersen and 17 to placebo. Mean concentrations of LDL cholesterol at baseline were 11·4 mmol/L in the mipomersen group and 10·4 mmol/L in the placebo group. The mean percentage change in LDL cholesterol concentration was significantly greater with mipomersen (−24·7%) than with placebo (−3·3%).

The most common adverse events were injection-site reactions in 76% of patients in mipomersen group vs 24% in placebo group. 12% of patients in the mipomersen group had increases in alanine aminotransferase of three times or more the upper limit of normal.

Inhibition of apolipoprotein B synthesis by mipomersen represents a novel, effective therapy to reduce LDL cholesterol concentrations in patients with homozygous familial hypercholesterolaemia who are already receiving lipid-lowering drugs, including high-dose statins.

References:
Mipomersen, an apolipoprotein B synthesis inhibitor, for lowering of LDL cholesterol concentrations in patients with homozygous familial hypercholesterolaemia: a randomised, double-blind, placebo-controlled trial. The Lancet, Volume 375, Issue 9719, Pages 998 - 1006, 20 March 2010.
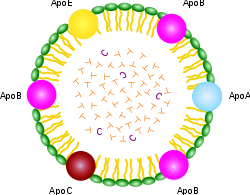
Lipoprotein structure (chylomicron) (left). Image source: Wikipedia, GNU Free Documentation License.

Sunday, May 2, 2010

Tiotropium for COPD: A good foundation therapy for most patients

From a BMJ Editorial:

Tiotropium is a once daily, inhaled, long acting anticholinergic drug (LAMA) that provides 24 hour improvement in airflow and hyperinflation in patients with chronic obstructive pulmonary disease (COPD).

Clinical trials have consistently shown that these physiological effects translate into improvements in:

- lung function
- exercise tolerance
- health related quality of life
- fewer exacerbations

References:
Tiotropium and chronic obstructive pulmonary disease. BMJ, 2010.
http://www.bmj.com/cgi/content/short/340/feb19_1/c833
Image source: Wikipedia, public domain.

Monday, April 26, 2010

Fish out of pills - Pharmaceuticals in drinking water


Fish out of pills - Pharmaceuticals in drinking water, NationalGeographic, April 01, 2010. Design Editor Oliver Uberti shows what went into the making of an information graphic about pharmaceuticals that make their way into our watersheds and end up in fish. Click here to see the full-size illustration.

A vast array of pharmaceuticals — including antibiotics, anti-convulsants, mood stabilizers and sex hormones — have been found in the drinking water supplies of at least 41 million Americans. The concentrations of these pharmaceuticals are tiny, far below the levels of a medical dose but the long-term consequences to human health are unknown.

The pharmaceutical industry points out the amount of medication in the water supply is the equivalent of a single pill in an Olympic-size swimming pool. Still, if you a have glass of water in Philadelphia, you are drinking tiny amounts of at least 56 medications.

References:
Antibiotics, anticonvulsants, antidepressants and sex hormones in drinking water of 41 million Americans http://goo.gl/HiXa
Pollution: Fish Pharm. NGM Blog Central.

Related reading:
Fish Pharm: Pharmaceutical Waste and the Environment. BitingTheDust, 2010.
Fishing For Answers: How To Choose Fish and Seafood | Summer Tomato http://goo.gl/0OBf

Updated: 05/02/2010

Sunday, April 25, 2010

FDA: High-dose simvastatin increases risk of muscle injury - caution with lower doses plus Amiodarone, Verapamil, Diltiazem

Based on review of data from a large clinical trial and data from other sources, the U.S. Food and Drug Administration (FDA) is informing the public about an increased risk of muscle injury in patients taking the highest approved dose of the cholesterol-lowering medication, Zocor (simvastatin) 80 mg, compared to patients taking lower doses of simvastatin and possibly other drugs in the "statin" class.

The muscle injury, also called myopathy, is a known side effect with all statin medications. The most serious form of myopathy is called rhabdomyolysis. Patients with myopathy generally have muscle pain, tenderness or weakness, and an elevation of a muscle enzyme in the blood (creatine kinase). The higher the dose of statin used, the greater the risk of developing myopathy. The risk of myopathy is also increased when simvastatin, especially at the higher doses, is used with certain drugs (see Simvastatin Dose Limitations below).

The data come from the SEARCH study, in which myopathy was seen in nearly 1% of patients taking the 80 milligram dose of Zocor but in only 0.02% of patients taking the 20 milligram dose of Zocor.

Update 6/2011: FDA Restricts Use of Simvastatin 80 mg, due to increased risk of muscle damage http://goo.gl/K9O5v

Rhabdomyolysis was rare in the SEARCH study. It happened in only 11 of 6,031 patients (0.02%) in group taking the 80 milligram dose of Zocor, but was not seen in patients taking the 20 milligram dose.

New data also suggest that people of Chinese descent should not take Zocor at the 80 milligram dose -- and should be careful even when taking lower doses -- if they also take niacin-containing products.

Simvastatin Dose Limitations

These limitations apply to ALL patients taking simvastatin.

Do not use simvastatin with these medications:

Itraconazole
Ketoconazole
Erythromycin
Clarithromycin
Telithromycin
HIV protease inhibitors
Nefazodone

Do not use more than 10mg of simvastatin with these medications:

Gemfibrozil
Cyclosporine
Danazol

Do not use more than 20mg of simvastatin with these medications:

Amiodarone
Verapamil

Do not use more than 40mg of simvastatin with this medication:

Diltiazem

References:
FDA Restricts Use of Simvastatin 80 mg, due to increased risk of muscle damage http://goo.gl/K9O5v
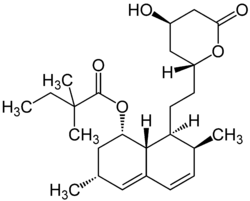
Image source: Simvastatin. Wikipedia, public domain.

Tuesday, April 20, 2010

AskaPatient.com - Medication Ratings and Health Care Opinions

This website "reports patient ratings and rankings of pharmaceuticals and prescription drug side effects. Database includes FDA-approved pharmaceuticals."

http://www.askapatient.com

You can Search by Drug Name:
http://www.askapatient.com/rateyourmedicine.htm

You can add ratings for the medications you take or look at ratings and comments from other patients.

For example:

cetirizine
http://www.askapatient.com/viewrating.asp?drug=19835&name=ZYRTEC

simvastatin (scores rather low)
http://www.askapatient.com/viewrating.asp?drug=19766&name=ZOCOR

Please note that I am not sure how useful the site is, and obviously, this post is not an endorsement or recommendation.

Related:
Image source: AskaPatient.com.

Saturday, March 20, 2010

FDA: Plavix does not work in 2-14% of patients

The FDA has put a new "black box" warning on the anti-clotting drug Plavix, the second best-selling drug in the world.

The new label warns that normal doses of Plavix have a potentially deadly lack of effect in 2% to 14% of patients.

Such patients are so-called "poor metabolizers" who carry a variant CYP2C19 gene affecting the enzyme that converts Plavix into its active form. The frequency is about 2% of Caucasians, 4% of blacks, and 14% of Chinese.

However, a 2010 study published in the NEJM contradicted the statement above:

It has been suggested that clopidogrel may be less effective in reducing the rate of cardiovascular events among persons who are carriers of loss-of-function CYP2C19 alleles that are associated with reduced conversion of clopidogrel to its active metabolite.

Among patients with acute coronary syndromes or atrial fibrillation, the effect of clopidogrel as compared with placebo is consistent, irrespective of CYP2C19 loss-of-function carrier status.

References:
New Plavix Warning: Lack of Effect in Many People. WebMD.
Effects of CYP2C19 Genotype on Outcomes of Clopidogrel Treatment. NEJM, 2010.
Image source: A box of Plavix. Wikipedia, Trounce, Creative Commons Attribution-Share Alike 2.5 Generic license.

Updated: 10/27/2010

Wednesday, February 17, 2010

People on statins are 9% more likely to develop diabetes according to a meta-analysis

From Reuters:

This small risk is outweighed by the drugs' heart-protecting properties but it could prompt a rethink among those with low cardiovascular risk factors who are tempted to take statins to prevent future heart disease.

"It will stop us putting statins in the water, as it were, and mean we give them when appropriate for the right reasons."

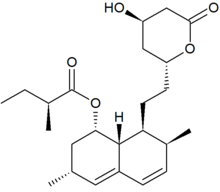
Lovastatin, a compound isolated from Aspergillus terreus, was the first statin to be marketed for lowering cholesterol. Image source: Wikipedia, public domain.

Statins are among the most successful drugs of all time and have been credited with preventing millions of heart attacks and strokes.

This Lancet meta-analysis included 13 large randomised controlled trials involving more than 91,000 patients.

Treating 255 patients with statins for 4 years would result in only one extra case of diabetes.

Giving statins to the same group would avoid 5.4 deaths or heart attacks over 4 years, and nearly the same number of strokes.

Clinical practice in patients with moderate or high cardiovascular risk or existing cardiovascular disease should not change.

References:
http://www.thelancet.com/journals/lancet/article/PIIS0140-6736(09)61965-6/fulltext

http://www.reuters.com/article/idUSTRE61G00P20100217

Related:
Statins Don't Cause Diabetes. Dr. Mintz' Blog.

Monday, October 19, 2009

Combination of ACE inhibitors and ARBs appeared no better than ACE inhibitor therapy alone and increased harms

From the Annals of Internal Medicine:

Ischemic heart disease (IHD) is the leading cause of death of both men and women in the U.S.

Angiotension-converting enzyme (ACE) inhibitors or angiotensin II receptor blockers (ARBs) are typically introduced when patients have heart failure or a heart attack with ventricular dysfunction.

Researchers reviewed 41 published studies to compare the benefits and harms of using ACE inhibitors, ARBs, or a combination of these treatments in adults with stable IHD and preserved ventricular function.

The researchers found that adding ACE inhibitors to standard treatment improves clinical outcomes in these types of patients. However, a combination of ACE inhibitors and ARBs appeared no better than ACE inhibitor therapy alone and increased harms.

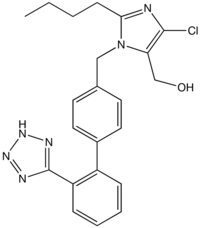
Image source: Losartan, the first ARB. Wikipedia, GNU Free Documentation License.

Sunday, October 4, 2009

Decreasing risk of death by 80% at the cost of $12 per month

High-risk patients who took 3 older drugs - statin, lisinopril, aspirin - cut risk of a heart attack or stroke by 80% (source: Reuters).

All of those are on the Walmart's $4 list which means you can decrease your risk of death by 80% for $12 per month (if you have the risk factors).

"Even in people who took it less than half the time, they got over a 60 percent drop in heart attacks and strokes," said Dr. R. James Dudl of Kaiser Permanente in California, whose study was published in the American Journal of Managed Care. "Those who took it more than half the time -- they got more like an 80 percent drop."It also suggests that people do not need to take a name-brand statin drug -- which Dudl said costs up to eight times more than a generic -- to achieve a major reduction in risks.

From Twitter:

Cameron Kaiserdoctorlinguist hey, lisinopril and lovastatin are $4 drugs at WalWart. cheap!

Ves Dimov, M.D.DrVes Yes. Pravachol (Pravastatin) is also $4.

Cameron Kaiserdoctorlinguist and benazepril! especially because in CA the 40mg lisinopril is *not* $4, for some reason .

References:
Cheap three-drug combination helps cut heart risks. Reuters.